Introduction: the silent progression of liver damage
The human liver is a chemical powerhouse, but it is not invincible. When the liver is subjected to chronic injury — most commonly from long-term alcohol use — it attempts to repair itself through scarring. What begins as liver fibrosis (early-stage scarring) can eventually harden into cirrhosis (late-stage failure).
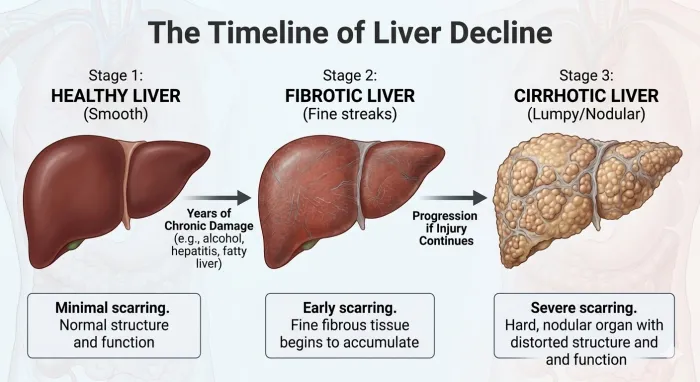
Fibrosis vs. alcoholic cirrhosis: the threshold of reversibility
Understanding where a patient stands on the liver health timeline is the difference between a lifestyle change and major surgery.
Liver fibrosis (warning phase)
The initial healing response of the liver — “internal calluses”. The liver structure is still mostly intact.
- Status: usually silent (no symptoms).
- Outcome: highly reversible if the cause (alcohol) is removed immediately.
Alcoholic cirrhosis (advanced phase)
Scarring is so dense that it chokes off blood flow. The liver becomes hard, shrunken and nodular.
- Status: noticeable symptoms (jaundice, swelling).
- Outcome: generally irreversible, requiring medical management or a transplant.
When is a liver transplant the only option?
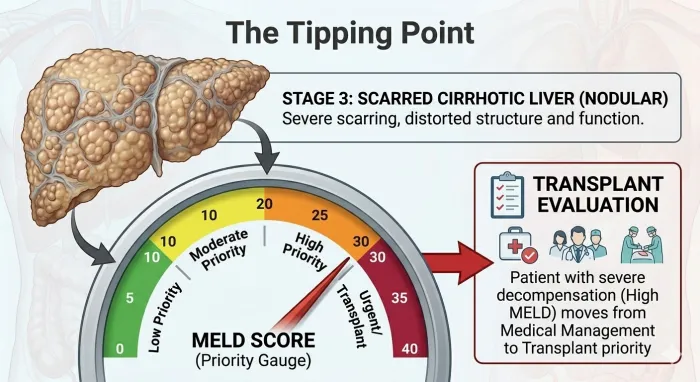
A transplant is considered when a patient moves into decompensated cirrhosis. At this point, the liver’s “backup systems” have failed.
The MELD score: how urgency is measured
Medical teams use the MELD score (Model for End-Stage Liver Disease) to prioritise patients. It is a calculation based on blood tests, including:
- Bilirubin: waste-processing levels
- INR: blood-clotting speed
- Creatinine: kidney health
The current US version, MELD 3.0, also includes sodium, albumin and sex. Calculate a MELD 3.0 score.
Clinical “red flags” for transplant
- Ascites: uncontrolled fluid build-up in the abdomen.
- Hepatic encephalopathy: mental confusion due to toxin build-up in the brain.
- Variceal bleeding: internal bleeding from veins in the oesophagus.
Eligibility: the road to the transplant waitlist
Because donor organs are a precious resource, the selection process is rigorous.
The “six-month rule” for sobriety
Most transplant boards require a minimum of 6 months of documented abstinence from alcohol before a patient is eligible for listing. This period allows the body to stabilise and shows commitment to protecting the new organ.
Comprehensive selection criteria
- Cardiopulmonary fitness: ensuring the heart and lungs can withstand a complex surgery of around 8 hours.
- Psychosocial readiness: evaluating the patient’s support system and mental-health stability.
- Nutrition: correcting the malnutrition often associated with chronic liver disease.
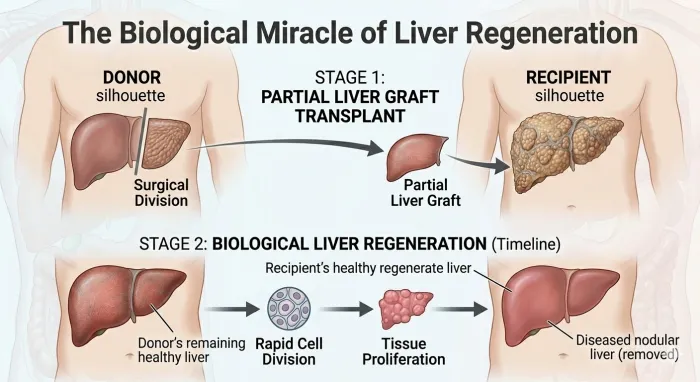
Types of procedures: living vs. deceased donors
Living donor transplant
A healthy relative donates a portion of their liver. Because the liver can regenerate, both the donor’s and the recipient’s liver portions grow to full size within weeks.
Deceased donor transplant
An organ is received from an individual who has passed away. These organs are allocated based on the severity of the recipient’s MELD score.
Life after transplant: success and maintenance
- Survival rates: 1-year survival is approximately 88–92%, while 5-year survival is roughly 75–82%.
- Immunosuppressants: lifelong medications are required to prevent the body from rejecting the new liver.
- The zero-alcohol rule: total abstinence is non-negotiable. Even a small amount of alcohol can damage the new graft.
Common questions
Can you get a liver transplant if you have alcoholic cirrhosis?
Yes. Alcoholic cirrhosis is a common indication for transplant. Eligibility is based on total sobriety, physical health and the ability to follow a strict post-operative medical plan.
How long is the ICU stay after a liver transplant?
Typically, patients spend 3 to 7 days in the ICU for stabilisation, with a total hospital stay of about 2 to 3 weeks.
What disqualifies you for a liver transplant?
Ongoing alcohol or drug use, severe heart, lung or kidney disease, active cancer outside the liver, and poor social support or inability to follow medical advice.
How long can a donor liver survive before a transplant?
A donor liver can survive 12–18 hours in cold storage, and up to 24 hours with advanced preservation.
What are the top 3 indications for liver transplant?
Alcoholic cirrhosis, viral hepatitis (B and C) and non-alcoholic fatty liver disease (NAFLD/NASH).
How does alcohol affect transplant eligibility?
Active drinking disqualifies patients. Relapse risk is carefully assessed, and commitment to lifelong abstinence is essential.
Conclusion: a commitment to a new beginning
Whether you are in the early stages of fibrosis or facing the complexity of a transplant, the liver offers a unique chance for a reset. Early detection and total abstinence from alcohol are keys to surviving liver disease.
“The surgery replaces the engine, but the patient provides the fuel. A successful transplant is a life-long partnership between the surgeon’s skill and the patient’s will.”