Quick answer
MELD 3.0 is a laboratory-based scoring formula, implemented by the US Organ Procurement and Transplantation Network (OPTN) on 13 July 2023, that predicts 90-day mortality risk for adults with chronic liver disease. It calculates a score from six inputs — bilirubin, creatinine, INR, sodium, albumin and sex — to prioritise patients on the liver transplant waiting list. It replaced MELD-Na largely to address reduced access to transplantation and higher risk of mortality or delisting among women under earlier formulas.
Key takeaways
- Standard for US adult liver allocation since 13 July 2023, adding albumin and sex to bilirubin, creatinine, INR and sodium.
- Designed to narrow the long-standing sex gap in transplant access.
- Score range: 6–40; higher means more urgent need — a prognostic tool, not a diagnostic one.
- Other countries use their own adapted models (e.g. GEMA-Na, reMELD-Na) rather than MELD 3.0 directly.
Introduction
If you or someone you love is being assessed for a liver transplant in the United States, you will almost certainly hear the term MELD 3.0. It is the formula clinicians use to rank patients on the transplant waiting list by how urgently they need a new liver. Understanding what goes into the score — and what changed from earlier versions — can make consultations with a hepatology team far less confusing.
What is MELD 3.0?

MELD 3.0 (Model for End-Stage Liver Disease, version 3.0) is a composite score used to predict mortality due to liver disease. It is the tool used by transplant centres across the United States to decide, among candidates on the waiting list, who receives priority when a donor liver becomes available.
The MELD family originated from work on using laboratory values to evaluate the severity of chronic liver disease — specifically three-month survival — to assess candidacy for transjugular intrahepatic portosystemic shunt (TIPS) placement. Its predictive strength for short-term mortality led to broader adoption, and the OPTN adopted MELD for national liver transplant allocation in 2002.
MELD 3.0 is the third major iteration. The score is a continuous scale with no fixed categories — organs go to the patient with the highest MELD in the compatible donor pool.
A brief history: from MELD to MELD 3.0
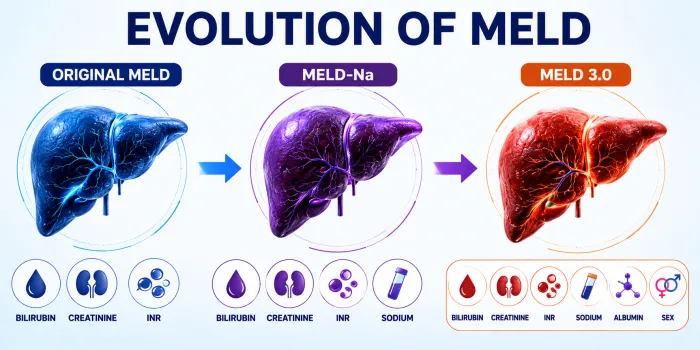
| Version | Introduced | Key variables | Main change |
|---|---|---|---|
| Original MELD | 2002 (national allocation) | Bilirubin, creatinine, INR | First laboratory-based, objective allocation score |
| MELD-Na | 2016 | Adds sodium | Corrected for hyponatraemia-related mortality risk |
| MELD 3.0 | July 2023 | Adds albumin and sex; revises coefficients | Improves accuracy and reduces sex-based disparity |
MELD-Na followed in 2016, incorporating sodium because lower sodium levels indicate a poorer prognosis. MELD 3.0 was proposed to improve on MELD-Na by adding sex and albumin, and by resetting the upper bound of serum creatinine to 3.0 mg/dL from 4.0 mg/dL. The OPTN Board approved the policy in mid-2022; Phase 1 on 15 June 2023 allowed programmes to enter required data, and Phase 2 — when MELD 3.0 began determining allocation — followed on 13 July 2023.
How the MELD 3.0 score is calculated
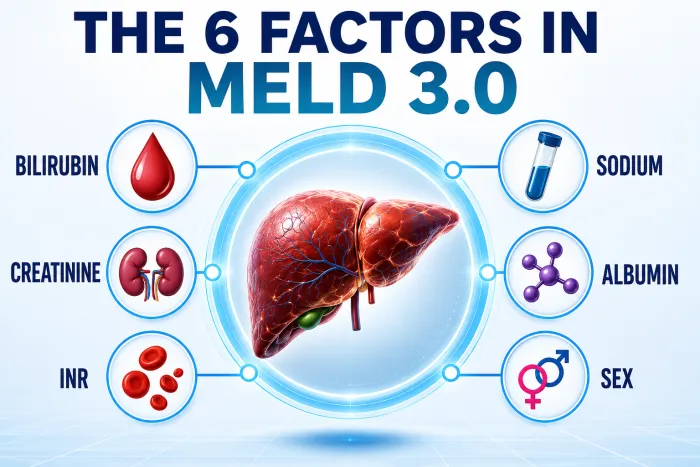
MELD 3.0 combines six clinical inputs into a single numerical score:
- Serum bilirubin (mg/dL)
- Serum creatinine (mg/dL)
- International Normalised Ratio (INR)
- Serum sodium (mmol/L)
- Serum albumin (g/dL)
- Sex (male or female)
According to the model developers, MELD 3.0 improves prediction accuracy by updating the coefficients for each variable, adding albumin, introducing interaction terms between variables, and lowering the maximum creatinine value from 4.0 to 3.0 mg/dL. Following long-standing MELD conventions, creatinine, bilirubin and INR values below 1.0 are set to 1.0, with a further cap applied for patients on dialysis.
The formula (Kim et al., 2021)
MELD 3.0 = 1.33 × (female) + 4.56 × ln(creatinine) + 0.82 × (137 − sodium) − 0.24 × (137 − sodium) × ln(creatinine) + 9.09 × ln(bilirubin) + 11.14 × ln(INR) + 1.85 × (3.5 − albumin) − 1.83 × (3.5 − albumin) × ln(creatinine) + 6
Bounds: creatinine 1.0–3.0 mg/dL (3.0 if on dialysis); bilirubin and INR minimum 1.0; sodium 125–137 mmol/L; albumin 1.5–3.5 g/dL. The result is rounded to a whole number and capped at 40.
The maximum MELD score under current OPTN policy is 40. In practice, few clinicians or patients work through the formula by hand — official calculators are provided by OPTN/UNOS and validated tools, with hospitals entering raw lab values directly.
MELD-Na vs. MELD 3.0: what actually changed
| Feature | MELD-Na | MELD 3.0 |
|---|---|---|
| Core labs | Bilirubin, creatinine, INR, sodium | Same four, plus albumin |
| Sex included | No | Yes |
| Creatinine ceiling | 4.0 mg/dL | 3.0 mg/dL |
| Coefficients | 2016 model | Re-estimated on more recent OPTN data |
| Interaction terms | None | Included between variables |
| Primary goal | Correct for hyponatraemia risk | Improve accuracy and reduce sex disparity |
Analysis of the OPTN registry treats these as distinct “MELD eras” for research purposes — MELD 1.0 (2002–2016), MELD 2.0/MELD-Na (2016–2022) and MELD 3.0 (2022–present).
Why sex and albumin were added
Before MELD 3.0, research consistently found women disadvantaged in transplant access relative to men with similar disease severity. A large nationwide cohort study found that women had reduced access to liver transplant (83.7% vs 85.9%) and an increased risk of mortality or delisting at 90 days, with female sex remaining an independent risk factor under MELD or MELD-Na but losing its statistical significance under GEMA-Na or MELD 3.0.
The disparity is partly biological and partly measurement-related: creatinine tends to under-represent reduced kidney function in people with lower muscle mass — disproportionately affecting women. Adding albumin and a direct sex adjustment helped correct for this. Early post-implementation analyses found MELD 3.0 decreased the sex disparity in probabilities of transplantation and waitlist death.
How MELD 3.0 scores are used in practice
MELD 3.0 does not determine transplant eligibility on its own — it determines priority among candidates already listed. General clinical guidance suggests considering referral to a hepatologist or liver transplant centre for patients with a MELD score of 10 or higher, though this threshold predates MELD 3.0 and centre practice varies.
Patients with hepatocellular carcinoma (HCC) may receive standardised “exception points” rather than relying solely on their calculated score, because many patients with early HCC have well-compensated cirrhosis and low MELD scores of 6–12, yet face significant risk from tumour progression if transplantation is delayed. Exception points follow defined OPTN criteria, including the Milan criteria.
Benefits and limitations
Benefits
- Improved fairness by sex: a narrowing gap in transplant access and waitlist mortality.
- Better statistical fit: objective, generalisable and easily verifiable variables.
- Retains simplicity: relies on routine blood tests.
- Transparent, continuous ranking: reduces arbitrary cut-off effects.
Limitations
- HCC: tumour risk doesn’t always track liver synthetic function.
- High scores: predictiveness may decrease above roughly 19 due to limited data at the extremes.
- International results are mixed: in Spain, GEMA-Na showed higher discrimination than MELD 3.0 for non-tumour candidates.
- Not validated for every use: e.g. major abdominal surgery or TIPS.
- Symptom burden isn’t fully captured: ascites and hepatic encephalopathy carry their own prognostic weight.
MELD 3.0 around the world
MELD 3.0 is a US-specific policy tool, developed and implemented through the OPTN. Other systems have adapted rather than adopted it: Germany introduced reMELD-Na in March 2025, while Spain developed GEMA-Na. If you’re researching liver transplant scoring outside the US, confirm which model your local network uses.
Common mistakes and misunderstandings
- Treating it as a diagnosis. It’s a prognostic and allocation tool, not a diagnostic test.
- Assuming a single lab draw is final. Scores are reassessed regularly and can change quickly.
- Confusing it with Child-Pugh. Child-Pugh includes clinical signs like ascites and encephalopathy directly; MELD 3.0 is laboratory-based.
- Assuming a “low” score means low risk. It doesn’t rule out complications like variceal bleeding, particularly with HCC.
- Believing MELD 3.0 is used globally. Several countries use their own formulas.
Frequently asked questions
What is a good MELD 3.0 score?
There’s no single “good” score — lower scores generally mean lower short-term mortality risk, but the score ranks candidates relative to each other rather than acting as a pass/fail threshold.
What is the highest MELD 3.0 score?
The maximum under current OPTN policy is 40.
Does MELD 3.0 apply to children?
No. Paediatric candidates use PELD or PELD-Cr instead.
Why was albumin added to MELD 3.0?
Albumin reflects liver synthetic function and nutritional status; its inclusion, alongside sex, improved predictive accuracy and helped correct earlier sex-based disparities.
Is MELD 3.0 used outside the United States?
Not directly as policy — several countries have their own adapted versions, such as GEMA-Na in Spain and reMELD-Na in Germany.
How is MELD 3.0 different from MELD-Na?
It adds serum albumin and sex, lowers the creatinine ceiling, updates the statistical coefficients and adds interaction terms between variables.
When did MELD 3.0 become the US standard?
Full implementation occurred on 13 July 2023, after a preparatory data-entry phase beginning 15 June 2023.
Can I calculate my own MELD 3.0 score at home?
Validated calculators exist, but scores should be interpreted by your transplant team, since exception points and comorbidities materially affect real-world prioritisation.
Does MELD 3.0 replace clinical judgement?
No — it’s one input among several, including exception-point systems for conditions like HCC.
Is MELD 3.0 the final version of this scoring system?
Unlikely. Given the pattern of prior revisions and ongoing research into refinements, further iterations are plausible as more outcome data accumulate.
Conclusion
MELD 3.0 is an evidence-driven refinement of how the United States prioritises patients for liver transplantation. By adding albumin and sex to bilirubin, creatinine, INR and sodium, it was built to correct a documented disparity that left women with lower transplant access and higher waitlist mortality. Like every version before it, it has acknowledged limits, particularly around HCC and very high-score patients. Use this article as a starting point for informed conversations with your transplant team, not as a substitute for their guidance.
References
- Kim WR, Mannalithara A, Heimbach JK, et al. MELD 3.0: The Model for End-Stage Liver Disease Updated for the Modern Era. Gastroenterology. 2021;161(6):1887–1895.
- Organ Procurement and Transplantation Network (OPTN). Liver allocation policy and MELD 3.0 implementation (June–July 2023). optn.transplant.hrsa.gov